Abstract
Background:
Novel Psychoactive Substances (NPS) emerged in the early 2000s as chemically designed alternatives to circumvent laws which internationally control drugs. There is limited evidence that NPS are produced in the UK, whereas China has long been recognised as a primary source of NPS. This study aimed to evaluate the relative impact of UK, Chinese, and UN legislative controls on the availability of NPS in the UK, as evidenced by post-mortem detections of NPS in deaths.
Methods:
Deaths reported to the National Programme on Substance Use Mortality (NPSUM) which occurred 2007–2022 were extracted for analysis. Drugs from the three major substance classes–opioids, stimulants and cannabinoids–which were detected in these deaths were categorised according to their control status as either classical substances (i.e., those under international control prior to 2007), NPS controlled in China, or other NPS.
Findings:
Across all three drug classes, detections of classical substances dominated throughout the study period. Detections of NPS opioids–primarily fentanyl analogues–peaked in 2017, NPS stimulants–notably cathinones–in 2015, and synthetic cannabinoid receptor agonists in 2018 and 2021. Whilst UK legislative controls (the Misuse of Drugs Act 1971, Temporary Class Drug Orders, the Psychoactive Substances Act 2016) were generally implemented first, reductions in NPS detections were more closely associated with the introduction of Chinese legislations - in particular the 2021 Chinese generic ban on synthetic cannabinoids which resulted in an almost complete disappearance of these compounds in UK deaths in 2022.
Conclusion:
The findings of this study indicate that the most effective way to reduce NPS availability in the UK is via legislation in producer countries, as evidenced by substantial declines in their detections in deaths following their control in China. This reliance on international controls places the UK in a vulnerable position, as its domestic drug landscape is being shaped largely by the pace and scope of independent international legislations. To achieve and maximise effectiveness, UK drug policy needs to integrate harm reduction measures alongside the introduction of legislative controls, whilst also encouraging international efforts to bring in global control of problem materials.
Highlights
Producer-country controls appear to be more effective than domestic legislation.
UK demand-side drug policy interventions appear to have had limited impact.
Control of NPS may be driving substitution to more harmful substances.
Introduction
Novel psychoactive substances (NPS) are drugs that have been newly designed to mimic the effects of traditional controlled substances (e.g., opioid, stimulants) (). They pose significant health risks due to their unknown potencies, toxic effects, and lack of pre-clinical and clinical testing (). There is very little evidence that NPS are manufactured within the United Kingdom (UK), with the UK NPS market instead supplied by imports of materials synthesised overseas: China has long been recognised as a primary source of NPS (; ; ; ; ; ), with the products of its extensive and proficient chemical industry infrastructure now readily available to the rest of the world by means of internet trading and rapid postal delivery services (; ; ).
Legal controls on NPS
Controls on NPS have been progressively introduced as new materials have emerged and evidence of their harms has accumulated (). Individual countries are responsible for legislative control of drugs within their jurisdiction. Additionally, there is overarching international drug control co-ordinated by the United Nations (UN), intended to provide a globally consistent approach (; ; ). UN guidance on materials for control are required to be enacted into national legislations of member states (; ; ).
UN guidance on regulation of NPS
The UN operates three major international Conventions addressing drug control: the 1961 Convention on Narcotic Drugs; the 1971 Convention on Psychotropic Substances; the 1988 Convention against Illicit Traffic in Narcotic Drugs and Psychotropic Substances (; ; ). These are updated annually by the UN Commission on Narcotic Drugs (CND), based on recommendations from the World Health Organisation’s (WHO) Expert Committee on Drug Dependence (ECDD). Since 2015, the annual extensions of the Conventions’ lists have primarily concerned NPS and their precursors.
UK legislative control of NPS
The UK as a UN member state is obliged to place substances listed in the three international drug Conventions under national drug control. The UK has also controlled many additional psychoactive substances which are considered to represent a hazard to human health (; ).
UK drug controls are primarily enacted by the Misuse of Drugs Act 1971 (the MDA ()). In addition to specific substances, the MDA also includes generic controls on families of psychoactive substances with a common core chemical structure intended to control ‘designer drugs’ – variants of controlled drugs chemically ‘designed’ so as to avoid specifically worded legislative controls ().
From 2009, as NPS began to emerge, a series of substance-specific and generic controls were brought into effect by means of additions to the MDA (e.g., synthetic cannabinoid receptor agonists [SCRAs], cathinones) (). However, such MDA additions took time to implement as evidence of substance-related harms needed to be gathered. The MDA was therefore supplemented by the use of emergency Temporary Class Drug Orders (TCDOs), introduced in November 2011 to permit more rapid control of NPS whilst their potential harms were more fully evaluated ().
However, as both the MDA and TCDOs require the identification of specific substances (or families of substances) to bring them under control, this proved a significant limitation to the control of rapidly emerging NPS. In response, the Psychoactive Substances Act 2016 (the PSA) was brought into effect in late May 2016 (). The PSA includes provisions to prevent the importation, distribution, and sale of any psychoactive substances which were outside the scope of the MDA and TCDO controls, unless specifically exempted (). This had the immediate effect of outlawing the open sale of NPS through commercial outlets such as ‘head shops’ and internet vendors ().
Chinese legislative control of NPS
China is also a UN member state and therefore a signatory of the three major international drug Conventions (; ; ). Similarly to the UK, China has also enacted a series of additional controls on a large number of specified NPS (; ) as well as a broad generic ban on fentanyl derivatives in May 2019 () and a set of generic controls on many SCRA structural families in May 2021 ().
Evolution of NPS
As substance-specific legislative controls have been introduced, NPS producers have rapidly adjusted their products or developed new NPS based on core structures not yet addressed by international or national controls (; ; ; ). This iterative process of new NPS, substance-specific legal controls, and rapid replacement by further NPS has become a game of “cat and mouse” or “whack-a-mole” (; ).
Study aim and method of investigation
In this study we aimed to evaluate the relative impact of UK, Chinese and UN control measures on NPS available on the UK illicit drug market. This evaluation was based on the most serious adverse effect of NPS, as evidenced by post-mortem detections of NPS in deaths from England, Wales and Northern Ireland recorded by the National Programme on Substance Use Mortality (NPSUM) over a 15-year period, from 2007 to 2022.
Methods
National programme on substance use mortality (NPSUM)
The NPSUM receives voluntary reports from over 85% of English, Welsh, Northern Irish and Islands’ (Jersey, Guernsey, Isle of Man) coroners on deaths related to psychoactive drugs. A death is referred to a coroner if it has an unknown cause, is violent or unnatural, sudden, and unexplained, occurred during an operation or before the person came out of an anaesthetic, or potentially caused by an industrial disease or poisoning (). Toxicology tests are requested dependent upon individual case circumstances at the discretion of the coroner and consulting pathologist.
A range of documents comprise coronial inquest files, although this varies from case to case. Typically, the coroner has access to: statements from witnesses, family and friends; General Practitioner (GP) records (if the deceased is registered with one); reports from first responders (e.g., police, emergency services); hospital emergency departments and clinical ward reports; psychiatric and substance abuse team reports; as well as post-mortem and toxicology reports. Information from these reports is transposed into the relevant data fields on the NPSUM database as either numerical variables or string text, as appropriate. All drugs detected by toxicological testing of post-mortem samples are entered on the NPSAD database, except for caffeine and nicotine (and metabolites thereof).
The King’s College London Biomedical and Health Sciences, Dentistry, Medicine and Natural and Mathematical Sciences Research Ethics Subcommittee re-confirmed in August 2025 that NPSUM does not require research ethics committee review as all subjects are deceased.
Case identification
A retrospective study design was used to identify all cases with detections of opioids, stimulants, or cannabinoids in post-mortem tissue (e.g., blood, urine, vitreous humor, stomach contents, liver, skeletal muscle) which occurred in the 15-year period 2007–2022 and were reported to the NPSUM by 1 November 2024. These three drug classes were chosen as the majority of additional controls enacted by the UK, China and UN have focused upon substances from within these classes (; ; ; ; ; ). Sub-analysis was then performed on cases with detections of opioids, stimulants, or cannabinoids which had been controlled in China between 2015 and 2021 either directly via legislation introduced by the Council of China, or indirectly via their addition to the International Drug Control Conventions by the UN Commission on Narcotic Drugs.
In the vast majority of cases, NPS detections were made from preserved blood and urine samples. UK toxicology laboratories typically screen for drugs using an immunoassay or a multi-analyte liquid chromatography–mass spectrometry (LC–MS) screening technique (). The samples then proceed to confirmatory testing using either an LC–MS/gas chromatography–mass spectrometry (GC–MS) or high-resolution accurate mass (HRAM) analysis ().
Data analysis
Software: Data analysis were performed using IBM® SPSS™ Statistics for Windows version 31, with visualisations constructed using Microsoft Excel 365.
Statistics: Given the time-series nature of the data and the close temporal proximity of when the UK, Chinese and UN NPS legislations were introduced, formal statistical testing was deemed to not be appropriate. The analyses are therefore descriptive, focusing on the temporal relationship between NPS detections in deaths and when the various NPS legislations were introduced.
Results
This study has been subdivided into three broad categories: opioids, stimulants, and cannabinoids. In the tables (Tables 1–3), the substances listed within each category have been segmented according to whether or not they were considered ‘classical’ substances. Classical substances are those that were under international control prior to the start of the study period (i.e., 2007). All other substances within each drug class have then been further segmented as to if and when they became controlled by China, and coloured coded as to when each was controlled by the UK, China and UN either in response to international guidance being issued or by means of a country-specific additional control.
TABLE 1
| Drug | Year | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 2007 | 2008 | 2009 | 2010 | 2011 | 2012 | 2013 | 2014 | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | ||
| Classical opioids | |||||||||||||||||
| Alfentanil | 0 | 0 | 1 | 0 | 1 | 1 | 1 | 2 | 0 | 2 | 4 | 2 | 3 | 4 | 7 | 13 |  |
| Buprenorphine | 8 | 6 | 11 | 15 | 12 | 12 | 27 | 36 | 41 | 34 | 52 | 63 | 82 | 104 | 101 | 98 | |
| Codeine | 214 | 227 | 321 | 270 | 257 | 258 | 284 | 279 | 282 | 307 | 286 | 387 | 354 | 367 | 420 | 386 | |
| Dextropropoxyphenea | 42 | 21 | 20 | 10 | 5 | 4 | 8 | 5 | 3 | 1 | 2 | 1 | 1 | 0 | 3 | 1 | |
| Dihydrocodeine | 131 | 140 | 136 | 103 | 128 | 101 | 103 | 105 | 129 | 112 | 100 | 130 | 146 | 157 | 146 | 134 | |
| Dihydromorphine | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 0 | 1 | 4 | 0 | |
| Dipipanone | 8 | 5 | 9 | 2 | 4 | 2 | 1 | 3 | 0 | 0 | 1 | 1 | 1 | 1 | 0 | 0 | |
| Etonitazene | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 4 | 5 | |
| Fentanyl | 7 | 5 | 13 | 11 | 18 | 18 | 31 | 26 | 44 | 52 | 86 | 63 | 72 | 59 | 51 | 53 | |
| Hydrocodone | 1 | 2 | 4 | 2 | 1 | 5 | 5 | 1 | 4 | 3 | 5 | 15 | 24 | 51 | 48 | 33 | |
| Levorphanol | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 1 | 0 | 0 | 2 | 0 | 0 | 1 | 0 | |
| Meptazinol | 2 | 4 | 0 | 1 | 0 | 1 | 0 | 0 | 1 | 0 | 1 | 5 | 0 | 2 | 3 | 3 | |
| Methadone | 380 | 369 | 437 | 390 | 446 | 345 | 353 | 331 | 398 | 382 | 401 | 478 | 577 | 856 | 826 | 793 | |
| Morphine/Heroin | 1029 | 1089 | 1305 | 812 | 672 | 677 | 674 | 844 | 990 | 991 | 931 | 1117 | 1380 | 1303 | 1295 | 1298 | |
| Oxycodone | 19 | 17 | 24 | 26 | 31 | 36 | 47 | 38 | 62 | 51 | 66 | 74 | 74 | 80 | 83 | 106 | |
| Oxymorphone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 4 | 2 | 1 | 1 | 4 | 7 | 2 | 0 | |
| Pentazocine | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Pethidine | 6 | 2 | 8 | 1 | 3 | 0 | 1 | 2 | 3 | 1 | 0 | 0 | 2 | 0 | 0 | 1 | |
| Remifentanil | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 0 | 1 | 1 | 1 | |
| Tramadol | 94 | 83 | 125 | 130 | 182 | 157 | 208 | 194 | 198 | 183 | 173 | 199 | 224 | 240 | 205 | 223 | |
| NPS opioids controlled in China in 2015 | |||||||||||||||||
| 4-Fluorobutyrylfentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 6 | 2 | 0 | 0 | 0 | 0 | |
| Acetylfentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 0 | 5 | 0 | 0 | 1 | 0 | 0 | |
| AH-7921 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Butyrfentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 6 | 1 | 1 | 0 | 0 | 0 | |
| Ocfentanil | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 0 | 0 | |
| NPS opioids controlled in China in 2017 | |||||||||||||||||
| Carfentanil | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 51 | 0 | 0 | 0 | 0 | 0 | |
| Furanylfentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 6 | 1 | 0 | 0 | 0 | 0 | |
| U-47,700 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| NPS opioids controlled in China in 2019 | |||||||||||||||||
| 2-Fluorofentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Cyclopropylfentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 2 | 0 | 0 | 0 | 0 | |
| Despropionyl fentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 3 | 1 | 1 | 0 | 0 | |
| Fluorofentanyl (unspecified) | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 0 | 0 | 0 | |
| Methoxyacetylfentanyl | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 7 | 0 | 2 | 1 | 0 | |
| NPS opioids controlled in China in 2021 | |||||||||||||||||
| Isotonitazene | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 17 | 2 | |
| Other opioids | |||||||||||||||||
| Brorphine | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | |
| Etodesnitazene | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 2 | |
| Kratom/Mitragynine | 0 | 0 | 0 | 0 | 0 | 4 | 2 | 0 | 4 | 1 | 0 | 0 | 1 | 0 | 1 | 1 | |
| N-Pyrollidino etonitazene | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 4 | 8 | |
| Protonitazene | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | |
| Tapentadol | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 2 | 1 | 2 | 5 | 8 | 15 | 13 | 10 | 20 | |
| Unidentified synthetic opioid | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | |
Detections of opioids in deaths reported to the NPSUM 2007–2022 subdivided by type (classical opioids; NPS opioids controlled in China in 2015, 2017, 2019, 2021; other opioids) and colour coded with year and jurisdiction of control according to the Colour Wheel of Drug Policy (yellow: UN; blue: UK; red: China; orange: UN and China; green: UN and UK; purple: UK and China; grey: UN, UK and China).
Considered as a licensed medication as previously licensed and prescribed.
TABLE 2
| Drug | Year | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 2007 | 2008 | 2009 | 2010 | 2011 | 2012 | 2013 | 2014 | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | ||
| Classical stimulants | |||||||||||||||||
| Amphetamine | 105 | 99 | 88 | 68 | 104 | 85 | 120 | 106 | 140 | 133 | 137 | 140 | 178 | 203 | 196 | 164 | 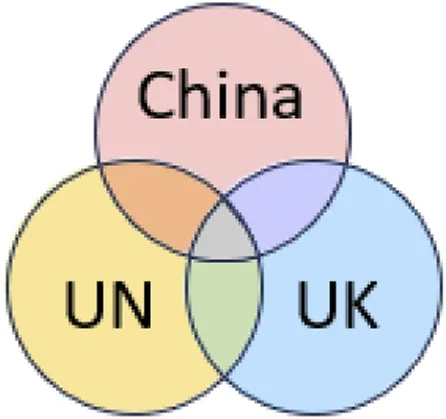 |
| Cathine | 0 | 3 | 1 | 0 | 0 | 1 | 0 | 1 | 1 | 1 | 1 | 2 | 1 | 0 | 7 | 1 | |
| Cathinone | 0 | 4 | 1 | 0 | 1 | 1 | 0 | 0 | 1 | 1 | 0 | 0 | 1 | 1 | 2 | 1 | |
| Cocaine | 427 | 422 | 341 | 232 | 236 | 264 | 335 | 398 | 502 | 597 | 756 | 938 | 1228 | 1371 | 1379 | 1779 | |
| DMT | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | |
| Fenproporex | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Methamphetamine | 6 | 6 | 3 | 3 | 6 | 7 | 10 | 11 | 8 | 11 | 15 | 17 | 25 | 37 | 43 | 37 | |
| Methylphenidate | 0 | 1 | 0 | 1 | 0 | 0 | 1 | 0 | 5 | 2 | 3 | 6 | 0 | 7 | 8 | 8 | |
| MDMA | 71 | 40 | 8 | 13 | 21 | 43 | 45 | 40 | 59 | 64 | 73 | 79 | 98 | 99 | 42 | 31 | |
| MDA | 0 | 1 | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 1 | 1 | |
| MDEA | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 1 | 5 | 2 | 2 | |
| N-Ethylamphetamine | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | |
| Para-methoxyamphetamine | 0 | 0 | 0 | 1 | 4 | 24 | 33 | 4 | 1 | 0 | 0 | 0 | 0 | 2 | 0 | 0 | |
| Phentermine | 1 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | |
| Pyrovalerone | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | |
| NPS stimulants controlled in China in 2015 | |||||||||||||||||
| 2-AI | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 1 | 1 | 1 | 1 | 1 | |
| 2-Methoxyphenidine | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 6 | 12 | 5 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 3-MMC | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 0 | |
| 3-Trifluoromethylphenylpiperazine | 4 | 3 | 22 | 14 | 5 | 3 | 3 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 0 | |
| 4-Fluoroamphetamine | 0 | 0 | 1 | 0 | 0 | 1 | 0 | 0 | 2 | 1 | 0 | 0 | 1 | 0 | 0 | 0 | |
| 4-Fluoromethamphetamine | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | |
| 5-MAPB | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 5-MeO-DALT | 0 | 0 | 0 | 1 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 5-MeO-DiPT | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Alpha-PHP | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 1 | 6 | 16 | 4 | |
| Alpha-PVP | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 4 | 8 | 0 | 1 | 1 | 0 | 3 | 3 | |
| AMT | 0 | 0 | 0 | 0 | 2 | 3 | 5 | 5 | 3 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Benzylpiperazine | 9 | 17 | 25 | 13 | 5 | 8 | 3 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | |
| Butylone | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 3 | 0 | 3 | 0 | 1 | 0 | 0 | 0 | |
| Clephedrone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 2 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Desoxypipradrol | 0 | 0 | 0 | 3 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| DOC | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | |
| Ethylone | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 2 | 3 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | |
| Ethylphenidate | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 20 | 10 | 1 | 0 | 1 | 0 | 0 | 1 | 0 | |
| Flephedrone | 0 | 0 | 0 | 2 | 2 | 3 | 0 | 0 | 2 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Fluoromethcathinone | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 2 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| MCPP | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 1 | 1 | 1 | 2 | 3 | 3 | |
| MDAI | 0 | 0 | 0 | 0 | 2 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| MDPBP | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| MDPV | 0 | 0 | 0 | 9 | 4 | 1 | 1 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | |
| Mephedrone | 0 | 0 | 7 | 46 | 25 | 25 | 30 | 32 | 34 | 7 | 4 | 5 | 4 | 3 | 8 | 2 | |
| Methedrone | 0 | 0 | 0 | 2 | 3 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 2 | |
| Methiopropamine | 0 | 0 | 0 | 0 | 0 | 4 | 8 | 16 | 18 | 6 | 1 | 0 | 0 | 0 | 1 | 0 | |
| Methylone | 0 | 0 | 0 | 2 | 0 | 4 | 9 | 3 | 1 | 0 | 1 | 0 | 0 | 2 | 0 | 0 | |
| Pentedrone | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| NPS stimulants controlled in China in 2016 | |||||||||||||||||
| 4-Methylethcathinone | 0 | 0 | 0 | 0 | 5 | 14 | 13 | 6 | 5 | 2 | 1 | 3 | 0 | 0 | 0 | 0 | |
| PMMA | 0 | 0 | 0 | 0 | 1 | 3 | 6 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | |
| NPS stimulants controlled in China in 2018 | |||||||||||||||||
| 4-Chloroethcathinone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 2 | 0 | 0 | 0 | 0 | |
| 4C-PVP | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | |
| 4-MEAPP | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 0 | 0 | 0 | 0 | 0 | |
| Dibutylone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 2 | 5 | 0 | 0 | |
| Ephylone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 4 | 2 | 1 | 0 | 0 | 0 | |
| MDPHP | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 11 | 15 | 1 | 3 | 4 | 7 | |
| Mexedrone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 7 | 1 | 0 | 0 | 0 | 1 | 0 | |
| Naphyrone | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| N-Ethylhexedrone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | |
| Pentylone | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | |
| NPS stimulants controlled in China in 2021 | |||||||||||||||||
| 1,2-Diphenidine | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 3-FPM | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 6 | 2 | 1 | 0 | 1 | 0 | 1 | 0 | |
| 3-MeO-PCP | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | |
| Eutylone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 4 | 0 | 0 | |
| Other stimulants | |||||||||||||||||
| 2-C-I | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 3-FMC | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 4-Ethylphenethylamine | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | |
| 4-Fluoromethylphenidate | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | |
| 4-Methylamphetamine | 0 | 0 | 0 | 0 | 1 | 2 | 2 | 5 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 5/6-APB | 0 | 0 | 0 | 0 | 1 | 4 | 3 | 1 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 5-IAI | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Aminoindane unspecified | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Atomoxetinea | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Benzedrone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | |
| CPP | 1 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 0 | 0 | 0 | 2 | 1 | 5 | 4 | 7 | |
| Desoxy-D2PM | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| DOI | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| EAPB | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Fluorocathinone | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Fluoropiperazine | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Ibogaine | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Methcathinone unspecified | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Methoxypiperamide | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | |
| Modafinila | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 1 | 0 | 1 | 3 | 2 | 4 | 1 | 4 | 3 | |
| Phenylpiracetamb | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | |
| Tryptamine unspecified | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 | 0 | |
Detections of stimulants in deaths reported to the NPSUM 2007–2022 subdivided by type (classical stimulants; NPS stimulants controlled in China in 2015, 2016, 2018, 2021; other stimulants) and colour coded with year and jurisdiction of control according to the Colour Wheel of Drug Policy (yellow: UN; blue: UK; red: China; orange: UN and China; green: UN and UK; purple: UK and China; grey: UN, UK and China).
Psychoactive medications not subject to the PSA.
Shown to act on CNS receptors but not formally tested for psychoactivity at time of writing so cannot be considered banned under the PSA
TABLE 3
| Drug | Year | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 2012 | 2013 | 2014 | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | ||
| Cannabis (THC) | 148 | 201 | 171 | 216 | 241 | 289 | 370 | 463 | 518 | 511 | 512 | |
| NPS synthetic cannabinoids controlled in China in 2015 | ||||||||||||
| 5F-AMB | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 1 | 1 | 0 | 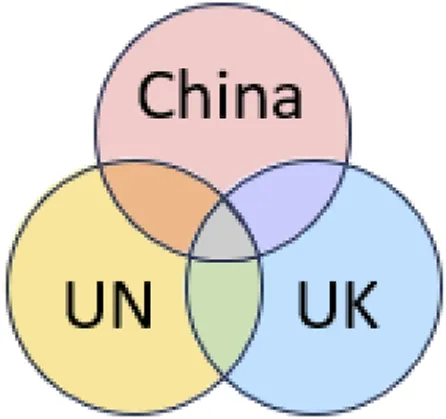 |
| 5F-APINACA | 0 | 2 | 3 | 5 | 2 | 0 | 0 | 0 | 0 | 0 | 0 | |
| 5F-PB-22 | 0 | 1 | 3 | 3 | 1 | 0 | 1 | 2 | 1 | 0 | 0 | |
| AB-CHMINACA | 0 | 0 | 1 | 2 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| AB-FUBINACA | 0 | 0 | 1 | 0 | 3 | 14 | 19 | 3 | 3 | 1 | 0 | |
| AB-PINACA | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 5 | 0 | |
| AKB-48 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| AM-2201 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| AM-2233 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| MDMB-CHMICA | 0 | 0 | 0 | 5 | 2 | 4 | 0 | 0 | 0 | 0 | 0 | |
| STS-135 | 0 | 0 | 3 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| NPS synthetic cannabinoids controlled in China in 2018 | ||||||||||||
| 5F-ADB | 0 | 0 | 0 | 0 | 8 | 37 | 50 | 5 | 3 | 1 | 1 | |
| ADB/AMB/EMB-FUBINACA | 0 | 0 | 0 | 0 | 0 | 4 | 4 | 0 | 0 | 3 | 0 | |
| NPS synthetic cannabinoids controlled in China in 2021 | ||||||||||||
| 4F-ABUTINACA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 9 | 0 | |
| 4F-AKB-48 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | |
| 4F-MDMB-BICA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 6 | 22 | 2 | |
| 4F-MDMB-BINACA | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 16 | 18 | 2 | 0 | |
| 5F-EMB-PICA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | 0 | |
| 5F-MDMB-PICA | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 22 | 14 | 3 | 0 | |
| 5F-MMB-PICA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | |
| ADB-4en-PFUPPYCA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | |
| ADB-4en-PINACA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | |
| ADB-BUTINACA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 33 | 1 | |
| ADB-HEXINACA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 3 | 0 | |
| APP-BINACA | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | |
| BB-22 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | |
| MDMB-4en-PINACA | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 11 | 41 | 23 | 7 | |
| MMB-CHMICA | 0 | 0 | 0 | 0 | 1 | 1 | 0 | 0 | 0 | 0 | 0 | |
| Other synthetic cannabinoids | ||||||||||||
| ADB-INACAa | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | |
| CHPIATAb | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 2 | |
| Unspecified SCRA | 0 | 0 | 0 | 2 | 1 | 9 | 8 | 0 | 0 | 1 | 0 | |
Detections of cannabinoids in deaths reported to the NPSUM 2007–2022 subdivided by type (cannabis [THC]; NPS synthetic cannabinoids controlled in China in 2015, 2018, 2021; other synthetic cannabinoids) and colour coded with year and jurisdiction of control according to the Colour Wheel of Drug Policy (yellow: UN; blue: UK; red: China; orange: UN and China; green: UN and UK; purple: UK and China; grey: UN, UK and China).
A “no-tail” SCRA, precursor so is not covered by generic legislations in China or the UK., Psychoactivity not yet proven so is not subject to the PSA.
Has an acetamide linkage so is not covered by the 2021 Chinese generic SCRA, control.
Opioids
Deaths with detections of opioids rose in the latter 5 years of the study (2018-2022) with an average of 560 deaths per year over 2007–2017, rising to 1,458 deaths in 2022 (Figure 1A). Classical opioids accounted for the majority of detections in these deaths (Figure 1B; Table 1).
FIGURE 1
There were no detections of NPS opioids before 2013 (Figures 1B, 2; Table 1). During the subsequent 10-year period, 2013 to 2022, within a total of 24,662 detections of opioids, 254 (1.0%) referred to NPS opioids. NPS opioid detections peaked in 2017 when there were 82 (3.8% of that year’s total detections), primarily driven by a cluster of detections of carfentanil (51 detections, 2.4% of the total).
FIGURE 2
Five NPS opioids were controlled in China in 2015, four due to specific controls enacted by the Council of China (4-fluorobutyrylfentanyl, acetylfentanyl, butyrfentanyl and ocfentanil) and one due to a UN directed control (AH-7921; Figure 2A; Table 1). Whilst detections of AH-7921 ceased following its ban, the other four NPS opioids controlled in China in 2015 persisted on the UK drugs market, with a peak of 18 detections in deaths occurring in 2017 before disappearing altogether in 2021. These four of NPS opioids had already been controlled for several years in the UK under the MDA (Table 1).
Three further waves of controls on NPS opioids were introduced in China in 2017, 2019, and 2021, with detections of the substances controlled reducing following their enaction (Figures 2B–D). All of the NPS opioids controlled by these Chinese legislations had already been controlled in the UK for several years under the MDA (Table 1).
Stimulants
Note: In this study, the ‘Ecstasy’ drugs, MDA, MDMA and MDEA, are not regarded as NPS as they were internationally controlled in 1985, 1986, and 1990 respectively (; ; ). During the study period, there was a marked contribution (69 cases) from para-methoxyamphetamine (PMA) detections. This material has been under international control since 1986 (; ; ), well before the period of interest, and is therefore not regarded here as an NPS. The closely related para-methoxy methamphetamine (PMMA) contributed a small number of reports (n = 11) concurrent with the PMA reports. PMMA has long been a controlled drug in the UK by virtue of the UK’s 1977 generic control on phenethylamine derivatives (). However, as it was not brought under international control until 2016 (; ; ), it is treated here as an NPS.
Deaths with detections of stimulants reported to the NPSUM have been steadily rising since 2013, with an average of 436 deaths per year over 2007–2012, rising to 1,581 deaths in 2022 (Figure 3A). Classical stimulants–and then mainly cocaine–accounted for the majority of detections in these deaths (Figure 3B; Table 2): in 2014, cocaine represented 59.3% of stimulant detections, which has risen to 86.4% of detections in 2022.
FIGURE 3
There were a total of 927 NPS stimulant detections within the study period, representing 6.0% of total stimulant detections. These reached a peak of 114 in 2015, but in the subsequent years in the study, 2016 to 2022, the average number of stimulant NPS detections dropped to approximately 40 per year.
In 2015, the Council of China controlled 116 NPS, 30 of which were stimulants detected in deaths reported to the NPSUM. Whilst 22 of these 30 substances were already controlled in the UK under the MDA (Table 2), it was not until this Chinese legislation was introduced in October 2015 that a considerable drop in detections of these 30 substances was observed (Figure 4A) – however, this drop does also somewhat coincide with the introduction of the PSA in the UK in May 2016. The only exception to this was in detections of alpha-PHP which briefly resurged in 2021 (n = 16).
FIGURE 4
Three further waves of controls on NPS stimulants were introduced in China in 2017, 2018, and 2021. Whilst detections of these NPS stimulants decreased following introduction of these controls (Figures 4B–D), in some instances decreases were apparent prior to their implementation (e.g., 4-methylethcathinone was controlled in 2016 but detections markedly decreased from 2013; 3-FPM was controlled in 2021 but detection markedly decreased from 2015). All of the NPS stimulants controlled by these Chinese legislations had already been controlled in the UK either under the MDA or PSA (Table 2).
Cannabinoids
Deaths with detections of cannabinoids reported to the NPSUM have been steadily rising since 2015, with an average of 149 deaths per year over 2007–2014, rising to 521 in 2022 (although peaking in 2020 at 571 deaths; Figure 5A). Once again, the ‘classical’ cannabinoid detections predominated–in this instance THC as the major psychoactive constituent of cannabis (Figure 5B). The NPS cannabinoids detected are all compounds that fall within the synthetic cannabinoid receptor agonist (SCRA) drug class.
FIGURE 5
There were no detections of SCRAs before 2012 (Figures 6A–D; Table 3). A total of 488 detections of 30 different SCRAs were reported to the NPSUM over the study period, first peaking in 2018 with 87 detections and then again in 2021 with 112 detections, before drastically falling in 2022 to 14 detections (from 12 deaths; Figure 6D; Table 3). Six SCRAs accounted for 63.5% of these detections: 5F-MDMB-PINACA (also known as 5F-ADB) 21.5%, MDMB-4en-PINACA 16.8%, AB-FUBINACA 9.0%, 5F-MDMB-PICA 8.2%, 4F-MDMB-BINACA 8.0% and ADB-BUTINACA 7.0%.
FIGURE 6
The first SCRAs were controlled in China in 2015, following which detections of those controlled dropped, except for AB-FUBINACA (Figure 6A; Table 3). Of the 11 SCRAs which were controlled in China in 2015 and which were detected in deaths, only two were already controlled in the UK under the MDA (Table 3).
Two further waves of controls on SCRAs were introduced in China in 2018 and 2021, with the 2021 legislation detailing a generic control on compounds featuring the skeleton SCRA structure. Detections of 5F-ADB and ADB/AMB/EMB-FUBINACA decreased following their control in China in 2018 (Figure 6B), as did detections of other SCRAs that had subsequently emerged following introduction of the 2021 generic SCRA control (Figure 6C). All of the SCRAs controlled by these latter Chinese legislations had already been controlled in the UK under the PSA (and many subsequently under the MDA; Table 3).
Discussion
In this study we have provided the first systematic evaluation of the relative impacts of UK, Chinese, and UN legislative controls on the availability of NPS in England, Wales and Northern Ireland, evidenced by their post-mortem detections in deaths following psychoactive drug use. By linking toxicological evidence to the introduction of drug control legislations across these jurisdictions, we were able to infer which regulatory controls were most effective in influencing the most negative effect (i.e., death) of NPS available on the UK drug market.
‘Classical’ substances remain the dominant drivers of drug-related mortality
A consistent finding across the three drug classes studied–opioids, stimulants and cannabinoids–is that classical substances were detected in the vast majority of deaths, eclipsing those with involvement of NPS. This illustrates that whilst NPS attract significant attention due to their novelty, unpredictable harms, and the challenges that they pose for regulators (; ; ; ; ), drug-related mortality continues to be driven by established, widely available substances (). Legislative controls on NPS have therefore not reduced overall demand for psychoactive substances, but rather reshaped the composition of the illicit drug market with a renewed consumption of classical substances.
UK vs. Chinese legislative impacts
Whilst the majority of UK legislative controls on NPS were enacted earlier than either the Chinese or UN equivalents, they appear to have had limited impact on the appearance of NPS in deaths. Instead, reductions in NPS detections correlated more with the introduction of Chinese controls. This is consistent with the central role that Chinese manufacturing and export networks are thought to hold in supplying the global NPS market (; ; ; ; ; ).
For NPS opioids, UK controls appear to have been largely ineffective, whereas the controls of these substances in China in 2017, 2019 and 2021 correspond with sharp reductions in their detection. An exception to this was the 2015 Chinese opioid controls, which were followed by a persistence of four non-pharmaceutical fentanyl analogues in deaths up until 2021. This anomaly could be due to a number of reasons, including that the 2015 controls represented one of the earliest and largest waves of Chinese NPS legislation () which may not have been enforced as comprehensively as subsequently introduced controls, that these fentanyl analogues may have been produced outside of China, or stockpiled materials within the UK. These explanations remain speculative however, in the absence of direct evidence. With regards to NPS stimulants, a similar pattern is evident: whilst the UK had already controlled the majority of cathinones under the MDA, there was only a marked drop in detections after China controlled many stimulant NPS in 2015. The clearest evidence of Chinese legislative impact was observed with cannabinoid NPS as the 2021 generic ban on SCRAs virtually eliminated the presence of these compounds in UK deaths within the year, reducing detections from over 100 to just 14 by 2022. In contrast, the earlier UK controls on SCRAs via the MDA and PSA had limited impact on the appearance of successive generations of SCRAs.
Taken together, these findings suggest that controlling NPS at their point of origin is more effective than restricting access and availability at the point of demand. This raises a pertinent and pressing question for future UK drug policy on emergent NPS: how can the UK move beyond a reactive position–dependent upon which NPS emerge from producer countries–to more proactively reduce the harms inflicted by the substances which ultimately reach its market?
Unanticipated consequences of NPS controls on market shifts
Prior to the implementation of the PSA, deaths with detections of cocaine were comparatively lower, suggesting that some NPS stimulants may be associated with a lower incidence of lethal toxicity than cocaine. Indeed, a number of pre-clinical studies have found several stimulant NPS–and particularly cathinone derivatives–to exert weaker dopaminergic activities when compared with cocaine (; ; ; ). Following the ban of stimulant NPS under the PSA, stimulant users appear to have returned to classical substances–and in particular cocaine–which was followed by a sharp rise in cocaine detections in deaths. A similar pattern was observed in Germany following the introduction of the Neue-psychoaktive-Stoffe-Gesetz (NpSG) in 2016 –legislation which generically controlled NPS rather than individual substances similar to the PSA–as there was a marked decline in the detection of NPS (; ; ) suggestive of a reduction in their domestic availability. However, subsequent studies have indicated that many German NPS users returned to using classical substances (; ), thus mirroring what was observed in the UK. This trend is illustrative of a recurring theme across drug markets which has been termed the ‘potency paradox’ (; ) in which restrictions on one substance/class of substances may be leading unintentionally to increased harms by steering users towards more potent alternatives. Indeed, the control of ketamine in the UK as a Class C substance in 2006 (and subsequently as a Class B substance in 2014) () was followed by the appearance of methoxetamine and diphenidines (; ), which were marketed as legal replacements to ketamine, but possess greater potency and longer duration of action (; ; ) leading them to be associated with more severe toxicological outcomes (). A related phenomenon is now playing out within the opioid drug class: although in this analysis NPS opioids represented only a fraction of detections, the subsequent widespread arrival of nitazenes in the UK in 2023 () after the end of the study period (note: the UK and China both implemented generic controls on nitazenes in 2025 (; ), however, it is not yet possible to assess the impact of these controls via analysis of drug deaths) has been linked to restrictions on less potent within-class alternatives (e.g., fentanyl analogues) and reduced heroin availability from Afghanistan (). Together, these findings highlight a central drug policy dilemma: whilst prohibition can reduce availability of NPS, it may also be a driver towards other more harmful substances, illustrating the need for complementary harm reduction strategies to be delivered alongside the implementation of legislative controls.
Strengths and limitations
This study has both strengths and limitations. A strength of this study is that it used routinely collated post-mortem toxicology data from the NPSUM, covering over 85% of coronial jurisdictions in England, Wales and Northern Ireland. This has provided a unique, mortality-based perspective of the NPS market, which is arguably one of the most clinically-relevant outcomes. However, the voluntary nature of reporting means that not all deaths, and therefore NPS detections, will have been captured. Furthermore, NPS toxicology screens are not requested in every case subject to coronial investigation, differ in terms of the screening library between laboratory operators, and will have happened at a particularly low incidence in the earlier years of the study when awareness of NPS was not as widespread. This may therefore have significantly impacted upon when NPS were first detected, as if not screened for they will not have been reported. However, as our analyses primarily focus on when NPS ceased to be detected in relation to legislative changes - by definition, such substances must have been previously included in analytical screens. The linking of mortality data to legislative implementations across multiple jurisdictions has allowed for stronger inference on the likely impact of different regulatory implementations. However, causality cannot be inferred with certainty: whilst temporal associations between NPS controls in China and reduced detections are strong, other market forces will have also contributed (e.g., law enforcement strategy, changing user preferences, price shifts). In this regard, it is important to note that NPS legislation introduced in India was not included as an additional variable in this analysis, despite India’s growing role as a producer of NPS (). This is because the legislations directing control of specific NPS in India were introduced either at the same time or after the same compounds had been directed for control under the UN Conventions, so that India, as a signatory of the Conventions, was obliged to enact controls (; ; ; ; ; ). Finally, as this analysis focused only on deaths, it has not captured trends in non-fatal NPS use. However, a recent UK study on acute recreational drug toxicity presentations in London which compared two time-points (2016/17 vs. 2019/20) had complementary findings to the present study as they observed a reduction in cathinone detections but no significant change in SCRA detections between these two timepoints (). This suggests that trends in non-fatal NPS toxicity presentations broadly reflect those observed in the mortality data.
Conclusion
The findings of this study indicate that the most effective way to reduce NPS availability in the UK is via legislation in producer countries, as evidenced by substantial declines in their detections in deaths following their control in China. UK interventions–despite enabling national law-enforcement activity and often being enacted earlier–had limited impact, highlighting the restricted influence of consumer country legislation in a globalised market. This reliance on international controls places the UK in a vulnerable position, as its domestic drug landscape is being shaped largely by the pace and scope of independent international legislations. To achieve and maximise effectiveness, UK drug policy needs to integrate harm reduction measures alongside the introduction of legislative controls, whilst also encouraging international efforts to bring in global control of problem materials. Without this combined approach, the cycle of NPS emergence, prohibition, and displacement will continue to undermine public health.
Statements
Data availability statement
Original data can be obtained from the corresponding author upon reasonable request. Requests to access these datasets should be directed to caroline.copeland@kcl.ac.uk.
Ethics statement
The requirement of ethical approval was waived by The King’s College London Biomedical and Health Sciences, Dentistry, Medicine and Natural and Mathematical Sciences Research Ethics Subcommittee for the studies on humans because NPSUM research does not require ethics committee review as all subjects are deceased. The studies were conducted in accordance with the local legislation and institutional requirements. Written informed consent for participation was not required from the participants or the participants’ legal guardians/next of kin in accordance with the national legislation and institutional requirements. The human samples used in this study were acquired from Pathologists who submitted samples to a toxicology laboratory for testing as part of the coronial investigation into the deaths. Written informed consent was not obtained from the individual(s) for the publication of any potentially identifiable images or data included in this article because all subjects are deceased so consent does not apply.
Author contributions
KR: Data curation, Visualization, Validation, Formal Analysis, Investigation, Writing – review and editing. RT: Investigation, Writing – review and editing, Conceptualization, Writing – original draft. CC: Formal Analysis, Resources, Writing – review and editing, Validation, Project administration, Writing – original draft, Visualization, Data curation, Methodology, Investigation, Conceptualization, Supervision.
Funding
The authors declare that financial support was received for the research and/or publication of this article. KLR is supported by a Society for the Study of Addiction PhD studentship.
Conflict of interest
The authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
Generative AI statement
The authors declare that no Generative AI was used in the creation of this manuscript.
Any alternative text (alt text) provided alongside figures in this article has been generated by Frontiers with the support of artificial intelligence and reasonable efforts have been made to ensure accuracy, including review by the authors wherever possible. If you identify any issues, please contact us.
Publisher’s note
All claims expressed in this article are solely those of the authors and do not necessarily represent those of their affiliated organizations, or those of the publisher, the editors and the reviewers. Any product that may be evaluated in this article, or claim that may be made by its manufacturer, is not guaranteed or endorsed by the publisher.
References
1
ACMD (2012). Statement of evidence: methoxetamine. 2012. Available online at: https://www.gov.uk/government/publications/statement-of-evidence-methoxetamine (Accessed September, 2025).
2
BaoY.MengS.ShiJ.LuL. (2019). Control of fentanyl-related substances in China. Lancet Psychiatry6 (7), e15. 10.1016/S2215-0366(19)30218-4
3
BiedermannN. (2017). How prohibition makes drugs more potent and deadly. Germany: Foundation for Economic Education. Available online at: https://fee.org/articles/how-prohibition-makes-drugs-more-potent-and-deadly/(Accessed September, 2025).
4
ChiappiniS.ClaridgeH.CorkeryJ. M.GoodairC.LoiB.SchifanoF. (2015). Methoxetamine-related deaths in the UK: an overview. Hum. Psychopharmacol.30 (4), 244–248. 10.1002/hup.2422
5
CorkeryJ. M.CopelandC.SchifanoF. (2025). Deaths related to the use of diarylethylamines, with a focus on the United Kingdom: a systematic review and case series report. J. Psychopharmacol., 2698811251349203. 10.1177/02698811251349203
6
DeenA. A.ClaridgeH.TrebleR. D.HamnettH. J.CopelandC. S. (2021). Deaths from novel psychoactive substances in England, Wales and northern Ireland: evaluating the impact of the UK psychoactive substances act 2016. J. Psychopharmacol.35 (11), 1315–1323. 10.1177/02698811211026645
7
Deventer MarieH.Krotulski AlexJ.Stove ChristopheP. (2025). Do It Yourself synthetic cannabinoid receptor agonist precursors as a ban-evading strategy: comparison of the pharmacological characteristics of precursors and their final products. Drug Test. Analysis17, 2148–2158. 10.1002/dta.3924
8
EUDA (2025). European drug report 2025: trends and developments. Available online at: https://www.euda.europa.eu/publications/european-drug-report/2025_en (Accessed September, 2025).
9
GomesA.RudkowskyT. (2025). playing Whack-a-Mole: a history of china’s drug bans. Talk. Drugs. Available online at: https://www.talkingdrugs.org/playing-whack-a-mole-a-history-of-chinas-drug-bans/ (Accessed September 2025).
10
gov.uk (2025). When a death is reported to a coroner. Available online at: https://www.gov.uk/after-a-death/when-a-death-is-reported-to-a-coroner (Accessed September, 2025).
11
GrothO.RoiderG.AngererV.SchäperJ.GrawM.MusshoffF.et al (2022). Spice-related deaths in and around munich, Germany: a retrospective look at the role of synthetic cannabinoids in our postmortem cases over a seven-year period (2014–2020). Toxicol. Anal. Clinique34 (3), S19. 10.1016/j.toxac.2022.06.323
12
HallF. S.MiczekK. A. (2019). Emerging threats in addiction: will novel psychoactive substances contribute to exacerbating the ongoing drug overdose epidemic?Psychopharmacology236 (3), 839–843. 10.1007/s00213-019-05271-7
13
HalterS.HaschimiB.MoglerL.AuwärterV. (2020). Impact of legislation on NPS markets in Germany - the rise and fall of 5F-ADB. Drug Test. Anal.12 (6), 853–856. 10.1002/dta.2786
14
HollandA.CopelandC. S.ShorterG. W.ConnollyD. J.WisemanA.MooneyJ.et al (2024). Nitazenes-heralding a second wave for the UK drug-related death crisis?Lancet Public Health9 (2), e71–e72. 10.1016/S2468-2667(24)00001-X
15
Home Office (2011). Temporary class drugs. Available online at: https://assets.publishing.service.gov.uk/media/5a79ba4b40f0b642860da492/temporary-class-drug-factsheet.pdf (Accessed September, 2025).
16
Home Office (2018). Review of the psychoactive substances act 2016. Available online at: https://www.gov.uk/government/publications/review-of-the-psychoactive-substances-act-2016 (Accessed September, 2025).
17
HorsleyR. R.LhotkovaE.HajkovaK.JurasekB.KucharM.PalenicekT. (2016). Detailed pharmacological evaluation of methoxetamine (MXE), a novel psychoactive ketamine analogue-Behavioural, pharmacokinetic and metabolic studies in the wistar rat. Brain Res. Bull.126 (Pt 1), 102–110. 10.1016/j.brainresbull.2016.05.002
18
JalalH.BurkeD. S. (2021). Carfentanil and the rise and fall of overdose deaths in the United States. Addiction116 (6), 1593–1599. 10.1111/add.15260
19
KellyJ. P. (2011). Cathinone derivatives: a review of their chemistry, pharmacology and toxicology. Drug Test. Anal.3 (7-8), 439–453. 10.1002/dta.313
20
KühnlR.AydinD.HornS.OlderbakS.VertheinU.KrausL. (2022). Taking the cat-and-mouse game to the next level: different perspectives on the introduction of the German new psychoactive substances act. Harm Reduct. J.19 (1), 122. 10.1186/s12954-022-00704-7
21
López-ArnauR.Martínez-ClementeJ.PubillD.EscubedoE.CamarasaJ. (2012). Comparative neuropharmacology of three psychostimulant cathinone derivatives: butylone, mephedrone and methylone. Br. J. Pharmacol.167 (2), 407–420. 10.1111/j.1476-5381.2012.01998.x
22
LuethiD.HoenerM. C.LiechtiM. E. (2018). Effects of the new psychoactive substances diclofensine, diphenidine, and methoxphenidine on monoaminergic systems. Eur. J. Pharmacol.819, 242–247. 10.1016/j.ejphar.2017.12.012
23
Ministry of Public Security of the People's Republic of China (2015). Notice of the ministry of public security, the state food and drug administration, the national health and family planning commission, and the office of the national narcotics control commission on the issuance of the measures for the regulation of non-medicinal narcotic drugs and psychotropic substances. Available online at: https://www.mps.gov.cn/n6557558/c5102861/content.html (Accessed September, 2025).
24
Ministry of Public Security of the People's Republic of China (2018). Announcement on the inclusion of 32 substances such as 4-chloroethcathinone in the supplementary list of controlled varieties of non-pharmaceutical narcotic drugs and psychotropic substances. Available online at: https://www.mps.gov.cn/n6557558/c6219874/content.html (Accessed September, 2025).
25
Ministry of Public Security of the People's Republic of China (2019). The three departments issued an announcement that fentanyl substances will be classified and controlled from may 1. Available online at: https://www.mps.gov.cn/n2254314/n2254487/c6473090/content.html (Accessed September, 2025).
26
Ministry of Public Security of the People's Republic of China (2021). Announcement on the inclusion of 18 substances such as synthetic cannabinoids and flutamines in the supplementary catalogue of non-medicinal narcotic drugs and psychotropic substances. Available online at: https://app.mps.gov.cn/gdnps/pc/content.jsp?id=7881703 (Accessed September, 2025).
27
Ministry of Public Security of the People's Republic of China (2025). The three departments jointly issued the announcement on listing 12 substances such as nichinoids and trifluoroethimidate in the. Available online at: https://www.mps.gov.cn/n6557558/c10115710/content.html (Accessed September, 2025).
28
Narcotics Control Bureau (2021). “Notification - fentanyls addendum,” in Ministry of home affairs GoI. Available online at: https://thehealthmaster.com/wp-content/uploads/2021/04/S.O.-1274-E-dt-23-03-2021-NDPS-Act-6-manufactured-drugs-added.pdf (Accessed October, 2025).
29
Narcotics Control Bureau (2015). “Notification,” in Ministry of home affairs GoI. Available online at: https://thehealthmaster.com/wp-content/uploads/2021/03/S.O.-375-E-and-376-E-dt-05-02-2015-Notification-Mephedrone-as-a-Psychotropic-Substance.pdf (Accessed October, 2025).
30
Narcotics Control Bureau (2017). “Annual report,” in Ministry of home affairs GoI. Available online at: https://narcoticsindia.nic.in/Publication/2017.pdf (Accessed October, 2025).
31
Narcotics Control Bureau. (2018). Notification. In: Ministry of home affairs GoI. Available online at: https://narcoticsindia.nic.in/legislation/rcsorder2103.pdf Accessed October 2025
32
Narcotics Control Bureau (2019). “Notification,” in Ministry of home affairs GoI. Available online at: https://thehealthmaster.com/wp-content/uploads/2021/03/G.S.R-215-E-dt-13-03-2019-NDPS-Rules-2019-amendment-Sr-No-27-to-33-substituted.pdf (Accessed October, 2025).
33
Narcotics Control Bureau (2021). “Notification,” in Ministry of home affairs GoI. Available online at: https://thehealthmaster.com/wp-content/uploads/2021/04/S.O.-1275-E-dt-23-03-2021-NDPS-Act-15-Psychotropic-substances-added.pdf (Accessed October, 2025).
34
National Statistics (2024). Deaths related to drug poisoning in England and Wales.
35
NormanC.LeeG. A. (2017). A snapshot of novel psychoactive substances (legal highs) use in London. Int. Emerg. Nurs.35, 56–58. 10.1016/j.ienj.2017.06.003
36
NuttD. (2020). New psychoactive substances: pharmacology influencing UK practice, policy and the law. Br. J. Clin. Pharmacol.86 (3), 445–451. 10.1111/bcp.14209
37
Opacka-JuffryJ.PinnellT.PatelN.BevanM.MeintelM.DavidsonC. (2014). Stimulant mechanisms of cathinones - effects of mephedrone and other cathinones on basal and electrically evoked dopamine efflux in rat accumbens brain slices. Prog. Neuropsychopharmacol. Biol. Psychiatry54, 122–130. 10.1016/j.pnpbp.2014.04.009
38
RinaldiR.BersaniG.MarinelliE.ZaamiS. (2020). The rise of new psychoactive substances and psychiatric implications: a wide-ranging, multifaceted challenge that needs far-reaching common legislative strategies. Hum. Psychopharmacol.35 (3), e2727. 10.1002/hup.2727
39
RooneyB.SobieckaP.RockK.CopelandC. (2023). From bumps to binges: overview of deaths associated with cocaine in England, Wales and northern Ireland (2000-2019). J. Anal. Toxicol.47 (3), 207–215. 10.1093/jat/bkad002
40
SeddonT. (2014). Drug policy and global regulatory capitalism: the case of new psychoactive substances (NPS). Int. J. Drug Policy25 (5), 1019–1024. 10.1016/j.drugpo.2014.03.009
41
SimmlerL. D.BuserT. A.DonzelliM.SchrammY.DieuL. H.HuwylerJ.et al (2013). Pharmacological characterization of designer cathinones in vitro. Br. J. Pharmacol.168 (2), 458–470. 10.1111/j.1476-5381.2012.02145.x
42
SommerM. J.HalterS.AngererV.AuwärterV.EyerF.LiebetrauG.et al (2022). Effect of new legislation in Germany on prevalence and harm of synthetic cannabinoids. Clin. Toxicol. (Phila).60 (10), 1130–1138. 10.1080/15563650.2022.2095282
43
ThorntonM. (1998). Potency of illegal drugs. J. Drug Issues.28 (3), 725–740. 10.1177/002204269802800309
44
UK Government (1971). Misuse of drugs act 1971. Available online at: https://www.legislation.gov.uk/ukpga/1971/38/contents (Accessed September, 2025).
45
UK Government. (2016). Psychoactive substances act 2016. Available online at: https://www.legislation.gov.uk/ukpga/2016/2/contents Accessed September 2025
46
United Nations Office (1971). United nations office on drugs and crime. Convention on psychotropic substances. Available online at: https://www.unodc.org/pdf/convention_1971_en.pdf (Accessed September, 2025).
47
United Nations Office on Drugs and Crime (1961). Single convention on narcotic drugs. Available online at: https://www.unodc.org/pdf/convention_1961_en.pdf (Accessed September, 2025).
48
United Nations Office on Drugs and Crime (1988). United nations convention against illicit traffic in narcotic drugs and psychotropic substances. Available online at: https://www.unodc.org/pdf/convention_1988_en.pdf (Accessed September, 2025).
49
UNODC (2025). July 2025 – china: announcement of class scheduling of 'nitazene' analogues 2025.
50
WallachJ.KangH.ColestockT.MorrisH.BortolottoZ. A.CollingridgeG. L.et al (2016). Pharmacological investigations of the dissociative 'Legal Highs' diphenidine, methoxphenidine and analogues. PLoS One11 (6), e0157021. 10.1371/journal.pone.0157021
51
WolfeC. E.SundL. J.ArcherJ. R.RoweA.HudsonS.WoodD. M.et al (2025). Comparison of laboratory confirmed drugs in acute recreational drug toxicity presentations to an urban hospital in London, UK, 2016/17 versus 2019/20. J. Med. Toxicol.21 (1), 25–29. 10.1007/s13181-024-01051-8
52
ZellnerT.EyerF.RabeC.GeithS.HaberlB.SchmollS. (2024). Recreational drug overdose-clinical value of toxicological analysis. Toxics12 (9), 662. 10.3390/toxics12090662
53
ZhaoM. (2020). Supply reduction policy against new psychoactive substances in China: policy framework and implementation. Int. J. Law, Crime Justice60, 100374. 10.1016/j.ijlcj.2019.100374
54
ZhaoM. (2022). The illicit supply of new psychoactive substances within and from China: a descriptive analysis. Int. J. Offender Ther. Comp. Criminol.66 (5), 495–516. 10.1177/0306624X19866119
Summary
Keywords
novel psychoactive substances, drug policy, international drug control, opioids, stimulants, cannabinoids
Citation
Rock KL, Treble R and Copeland CS (2026) Legislating novel psychoactive substances: lessons from 15 years of UK mortality data (2007-2022). Front. Pharmacol. 16:1708335. doi: 10.3389/fphar.2025.1708335
Received
18 September 2025
Revised
24 October 2025
Accepted
20 November 2025
Published
29 January 2026
Volume
16 - 2025
Edited by
Taoufik Ghrairi, Tunis El Manar University, Tunisia
Reviewed by
Heather Barkholtz, University of Wisconsin-Madison, United States
Tobias Zellner, Technical University of Munich, Germany
Updates
Copyright
© 2026 Rock, Treble and Copeland.
This is an open-access article distributed under the terms of the Creative Commons Attribution License (CC BY). The use, distribution or reproduction in other forums is permitted, provided the original author(s) and the copyright owner(s) are credited and that the original publication in this journal is cited, in accordance with accepted academic practice. No use, distribution or reproduction is permitted which does not comply with these terms.
*Correspondence: Caroline S. Copeland, caroline.copeland@kcl.ac.uk
Disclaimer
All claims expressed in this article are solely those of the authors and do not necessarily represent those of their affiliated organizations, or those of the publisher, the editors and the reviewers. Any product that may be evaluated in this article or claim that may be made by its manufacturer is not guaranteed or endorsed by the publisher.